
Summary
What is 17-hydroxyprogesterone (17-OHP)?
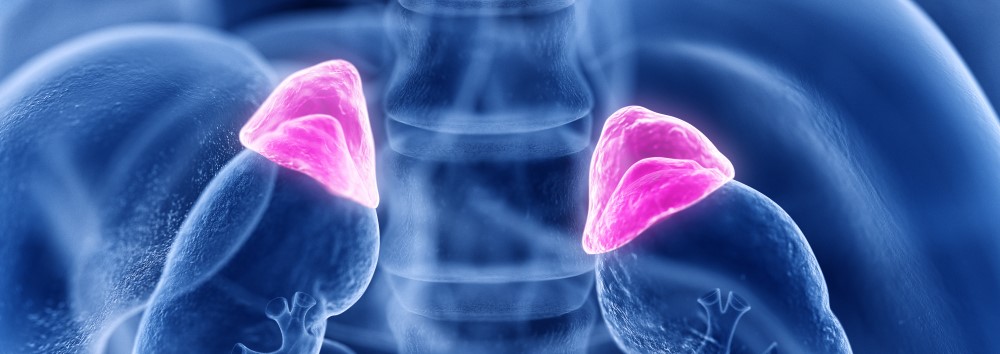
Your adrenal glands, which sit on top of your kidneys, make several important hormones, including:
The adrenal glands make hormones through a series of steps that begin with cholesterol. Cholesterol is synthesised into 17-hydroxyprogesterone (17-OHP). Next, three different pathways lead to the production of cortisol, aldosterone and sex hormones.
Along each pathway, several enzymes are needed to convert one substance into another. One of the most important of these is an enzyme called 21-hydroxylase.
What is congenital adrenal hyperplasia (CAH)?
Congenital adrenal hyperplasia (CAH) is a group of inherited disorders affecting these pathways. CAH occurs when someone inherits altered copies (variants) of a gene that controls one of these enzymes. About 95% of cases are caused by variants in the CYP21A2 gene, which controls the production of 21-hydroxylase. Data from newborn infants screened worldwide show an overall prevalence of about 1 in 14,000 to 1 in 18,000 births.
21-hydroxylase is needed to convert 17-OHP to cortisol and aldosterone. If you do not have enough of this enzyme, or it does not work properly, 17-OHP builds up and the excess is instead diverted into the pathway that makes male sex hormones (androgens).
The result is that not enough cortisol and sometimes not enough aldosterone are made while too much male sex hormone is made.

Two forms of CAH - classic and non-classic
Classic CAH
Classic CAH, also known as 21-hydroxylase deficiency CAH, is a serious potentially life-threatening condition usually diagnosed in babies. It is a form of CAH in which 21-hydroxylase is not produced in the body. In Australia, newborn babies are routinely screened for classic CAH as part of the newborn bloodspot (heel-prick) screening program.
Babies with CAH can experience what is called a salt-wasting crisis. If CAH affects aldosterone production it causes a loss of sodium and water in the urine which leads to dehydration, low blood pressure and changes in sodium and potassium levels. Early diagnosis and treatment with replacement hormones can prevent this.
Female babies can be born with ambiguous genitalia, meaning it can be difficult to tell at birth if they are male or female.
Newborn screening for CAH usually starts by measuring 17-hydroxyprogesterone (17-OHP).
Non-classic CAH
Non-classic CAH is a milder form of CAH in which 21-hydroxylase still works, but less effectively. It may not become apparent until later childhood, adolescence or adulthood.
In girls and women, it can cause excess facial or body hair, irregular periods and sometimes infertility. In boys, it can cause early development of sexual characteristics (precocious puberty), while adult men may experience infertility.
Why get tested?
Diagnosis
Measuring levels of 17-OHP in a sample of blood can show if levels are high which can help diagnose CAH.
Monitoring
CAH is usually treated with steroid medicines to replace the cortisol that the adrenal glands cannot adequately make. In more severe forms, treatment also includes replacing aldosterone and increasing salt intake, particularly in babies and young children, to maintain normal salt and fluid balance. Treatment also helps reduce the amount of male sex hormones (androgens) being produced. 17-OHP testing can be used regularly to check how well your treatment is working.
Polycystic ovary syndrome (PCOS)
17-OHP testing can be included when investigating symptoms of polycystic ovary syndrome (PCOS). It is used to rule out non-classic CAH, which can cause similar symptoms, such as excess facial or body hair, irregular periods and difficulty becoming pregnant.
Genetic Testing
Genetic testing is generally used to confirm or clarify a diagnosis. It can be particularly useful when 17-OHP and other hormone test results are unclear, or when the type of CAH needs to be confirmed. It does not replace 17-OHP and other hormone testing.
About 95% of CAH is caused by a mutation, known as a variant, in the CYP21A2 gene, which controls 21-hydroxylase. Almost 200 different CYP21A2 mutations have been identified. There are also rarer forms of CAH that are caused by variants in other genes. Genetic testing panels may also include genes such as CYP11B1, associated with 11-beta-hydroxylase deficiency, and CYP17A1, associated with 17-alpha-hydroxylase deficiency.
Different CYP21A2 variants affect how well 21-hydroxylase works. Variants that cause little or no enzyme activity are generally associated with the more severe classic CAH. Variants that allow some enzyme activity are more often associated with milder, non-classic CAH.
However, genetic results cannot always predict severity, as people with similar variants can have different symptoms.
How CAH is inherited
Everyone has two copies of each of their genes—one copy inherited from each parent. If someone inherits a variant on one of the two gene copies, the other still works.
21-hydroxylase deficiency CAH is inherited in an autosomal recessive way. This means you need to inherit an altered copy of the CYP21A2 gene from both parents.
If you inherit only one altered copy, you are a carrier. Carriers usually do not have CAH because their other working copy of the gene produces enough 21-hydroxylase enzyme.
Parents may be carriers, and carriers may not have any signs of the disorder. If both parents are carriers, then each child has a 25% chance of having the condition.
If variants are found in both copies of the CYP21A2 gene, this can confirm a diagnosis of 21-hydroxylase deficiency.
Reproductive carrier screening
CAH can be included in expanded genetic reproductive carrier screening performed before or during pregnancy. If both parents are carriers of a genetic change causing the same form of CAH, there is a 1 in 4 (25%) chance with each pregnancy that their child will have the condition.
Chromosome studies
A karyotype (chromosome studies) may be ordered as a follow-up test. This looks at the number and structure of a person's chromosomes, including the sex chromosomes (XX or XY) which can be useful when a newborn has genitalia that are not clearly typically male or female. For more on chromosomes see karyotyping.
Having the test
Sample
Blood
Any preparation?
None
Your result
This is less clear. If you have moderately increased levels, you may have a less severe case of CAH or an 11-beta-hydroxylase deficiency (another enzyme defect associated with CAH) or may have a false positive test. 17-OHP can be temporarily raised by illness or physical stress and is naturally higher in newborn babies. In women, levels also change during the menstrual cycle. A raised result therefore does not necessarily mean you have CAH. In a person being treated for CAH, a low or decreasing level of 17-OHP indicates the treatment is working while a high or increasing level may indicate that changes in treatment are required. Premature infants often have elevated levels of 17-OHP. The test may need to be repeated at a later time.17-OHP result What this may mean Normal (within the reference interval) This usually makes 21-hydroxylase deficiency unlikely. However, if there is still a strong suspicion of congenital adrenal hyperplasia (CAH), further testing may be needed. Slightly or moderately raised
If your result is borderline or moderately raised, the test can be repeated. Very high An increased level indicates 21-hydroxylase deficiency.
Levels are usually much higher in the severe, classic forms of CAH than in the milder, non-classic form.
If a newborn or infant has significantly elevated concentrations of 17-OHP, then it is likely that they have CAH. Short synacthen (ACTH stimulation) test Your 17-OHP is measured before and after synacthen is given. A large rise in 17-OHP supports a diagnosis of 21-hydroxylase deficiency. For more see short synacthen test
Reading your test report
Your results will be presented along with those of your other tests on the same form. You will see separate columns or lines for each of these tests.
Reference intervals - comparing your results to the healthy population
Your results will be compared to reference intervals (sometimes called a normal range).
If your results are flagged as high or low this does not necessarily mean that anything is wrong. It depends on your personal situation.
Reference intervals for 17-OHP vary between laboratories in Australia because they use different measurement instruments.
Questions to ask your doctor
The choice of tests your doctor makes will be based on your medical history and symptoms. It is important that you tell them everything you think might help.
You play a central role in making sure your test results are accurate. Do everything you can to make sure the information you provide is correct and follow instructions closely.
Talk to your doctor about any medications you are taking. Find out if you need to fast or stop any particular foods or supplements. These may affect your results. Ask:
More information
Pathology and diagnostic imaging reports can be added to your My Health Record. You and your healthcare provider can now access your results whenever and wherever needed.
Get further trustworthy health information and advice from healthdirect.
What is Pathology Tests Explained?
Pathology Tests Explained (PTEx) is a not-for profit group managed by a consortium of Australasian medical and scientific organisations.
With up-to-date, evidence-based information about pathology tests it is a leading trusted source for consumers.
Information is prepared and reviewed by practising pathologists and scientists and is entirely free of any commercial influence.








