
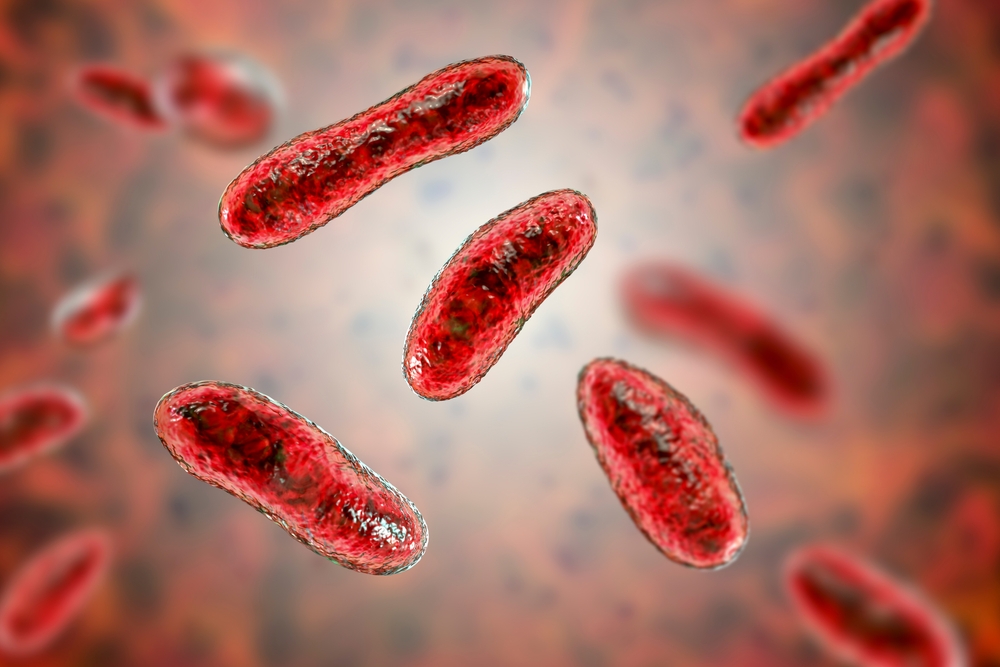
Q fever is an infection carried by animals, including farm animals such as cattle, sheep and goats and some wild and domestic animals including kangaroos. Infected animals usually appear healthy and show no signs of illness though can experience pregnancy loss.
Q fever is caused by Coxiella burnetii bacteria that are shed in the faeces, urine and milk of infected animals. The bacteria are extremely hardy and can survive in dust and soil for many months, and sometimes years. They can easily spread over long distances on the wind, and only a few infectious particles are needed to cause illness.
Humans can become infected by the bacteria through close contact with infected animals and those whose work brings them into regular contact with animals or contaminated environments are most at risk.
In most cases, people become infected by breathing in contaminated dust or tiny droplets while handling infected animals or working in a contaminated environment. The risk is highest during animal births because the placenta, birth fluids and other birthing tissues contain very high numbers of bacteria. As a result, people involved in breeding animals or assisting with animal births are at particularly high risk. Anyone living or working close to farms and abattoirs are also at increased risk.
The bacteria are mainly spread between animals by ticks. Ticks can transmit the bacteria to people although this is uncommon, and Q fever is generally not considered to be a tickborne disease. Person to person spread of the infection is extremely rare.
Q fever was discovered in 1935 by Australian pathologist Edward Derrick after an outbreak of unexplained fevers among abattoir workers in Brisbane. Derrick named it Q fever, Q standing for ‘query’ because he did not know what was causing the infection. Coxiella burnetii was later named after Australian immunologist Professor Frank Macfarlane Burnet who isolated it in 1937. The bacteria were later discovered in ticks in the United States (in the early 1940s). It is present in all countries worldwide except New Zealand and Antarctica.

Q fever is challenging for doctors to diagnose. Symptoms vary from person to person and it also can be difficult to distinguish Q fever from other illnesses.
Acute Q Fever
Acute Q fever is the term used for the initial infection. Many people have no symptoms, but those who do usually develop a severe flu-like illness about 2 to 3 weeks after being exposed to the bacteria.
Common symptoms include:
Some people develop pneumonia or inflammation of the liver (hepatitis). These can last from 2 to 6 weeks. A mild skin rash can also occur, but this is uncommon. Serious complications are rare. In a few people, the infection can affect the heart, the lining around the heart (called the pericardium), the brain, the spinal cord or the testicles. Q fever in pregnancy can increase the risk of miscarriage, premature birth or having a baby with a low birth weight.
Most people recover completely, although it may take several weeks to months before they feel back to normal.
Chronic Q fever
A few people develop what is called persistent, focalised or chronic Q fever, a long-term infection that can occur months or even years after the initial illness. In some cases, it develops in people who hadn’t realised they had acute Q fever.
Chronic Q fever happens when the bacteria remain in the body and continue to cause infection. It most commonly affects:
People who are at higher risk of developing chronic Q fever include those who have damaged or artificial heart valves, an aneurysm, an artificial blood vessel (vascular graft), have a weakened immune system or are pregnant.
Those who are at risk for developing a chronic infection are usually required to have regular bloods tests several years after acute infection to monitor antibody changes.
Post-Q fever fatigue syndrome
Persistent fatigue for up to a year is common post-acute infection. Some people continue to have symptoms for more than 12 months after recovering from the initial Q fever infection. This is known as post-Q fever fatigue syndrome. It is the most common long-term effect of acute Q fever in Australia, affecting about 10–15% of people who have the infection.
The most common symptom is extreme tiredness that does not improve with rest. Other symptoms can include joint and muscle pain, concentration and memory problems, sleeping problems, heavy sweating and headaches.
A vaccine for Q fever is available and highly recommended if you work in a high-risk occupation. Vaccination is also recommended for everyone aged 15 years or more who has the potential to be exposed in the environments in which they live or visit.
Before having the Q fever vaccine
People who have previously had Q fever or have already received the Q fever vaccine should not be vaccinated again. This is because their immune system has already developed strong immunity to the bacteria. If they are vaccinated again, their immune system can react too strongly to the vaccine, causing severe local or systemic reactions. These reactions can be much worse than the mild side effects seen in people receiving the vaccine for the first time.
Before vaccination, everyone is screened for previous exposure to Q fever. This includes:
If any of these screening tests are positive, the vaccine should not be given.
The Q fever vaccine provides long-lasting protection, and booster doses are not recommended because they can cause serious reactions in people who already have immunity from a previous infection or vaccination.
Two types of tests are used to diagnose and monitor Q fever. They work in different ways. They are:
PCR tests (direct testing)
PCR is a genetic test that detects the DNA of the bacteria. It is most useful early in the illness after you have first been infected or in persistent focalised (chronic) infection.
Serology tests (indirect testing)
These are tests that look for the antibodies your immune system makes to fight the bacteria. Your immune system protects you by making antibodies to attack substances that are foreign to your body and could be harmful to you. This includes infections like bacteria and viruses.
It does this by targeting marker antigens which are found on the surfaces of most cells. Cells with marker antigens that are different from your own can be attacked. Each antibody is made to recognise and attach to only one target antigen, or a very small group of closely related targets.
Why are both tests needed?
PCR testing is useful during the early stage of illness. Serology tests show how your immune system is responding to the infection.
PCR only detects the bacteria for a short time. In acute infection, the bacteria can usually be detected in the blood for up to about 2 weeks after symptoms begin. After this, PCR is often negative even if you have Q fever.
Antibodies take time to develop. Your immune system usually starts producing detectable antibodies about 1 to 3 weeks after symptoms begin. Serology tests look for these antibodies rather than the bacteria itself. In the first few days of illness, there may not yet be enough antibodies to detect, so an antibody test can be negative even if you are infected.
Sample
Blood
Any preparation?
None
Acute Q fever (initial infection)
Antibodies to Coxiella burnetii take longer to develop than in many other bacterial infections. In the first 2 weeks after you have been infected, although Coxiella burnetii are circulating in the bloodstream, levels of antibodies are very low. A PCR blood test can detect the bacteria’s DNA during the first two weeks after symptoms begin. It is very good at finding the infection early. However, a negative PCR result does not rule out Q fever. This is because the bacteria are only detectable in the blood for a short time.
Serology testing looks at 3 Coxiella burnetii-specific antibodies:
Two blood samples need to be collected and tested. Doctors usually request:
A fourfold rise in IgG antibodies between the first and second sample tested confirms recent infection.
Because antibodies take time to develop, your treatment will usually be started before your test results are ready.
The pattern of antibodies can help decide whether the infection is:
It helps guide treatment and follow-up. If you have chronic Q fever you may need prolonged antibiotic treatment, so identifying the antibody pattern is important.
Chronic Q fever (later symptoms)
Interpreting Q fever antibody (serology) test results can be complicated because the pattern of antibodies changes over time. Because these antibody patterns can be difficult to interpret, laboratories and doctors use reference tables and seek expert advice when needed. If Q fever causes complications (like hepatitis or endocarditis), further tests and scans will often be ordered.
Because Q fever symptoms are similar to many other infections, your doctor may also order tests to check for other possible causes of your illness, such as influenza (flu), COVID-19, glandular fever, pneumonia, or other bacterial and viral infections.
The choice of tests your doctor makes will be based on your medical history and symptoms. It is important that you tell them everything you think might help.
You play a central role in making sure your test results are accurate. Do everything you can to make sure the information you provide is correct and follow instructions closely.
Talk to your doctor about any medications you are taking. Find out if you need to fast or stop any particular foods or supplements. These may affect your results. Ask:
Pathology and diagnostic imaging reports can be added to your My Health Record. You and your healthcare provider can now access your results whenever and wherever needed.
Get further trustworthy health information and advice from healthdirect.